
How Much Does Medicaid Spend on Gender-Affirming Care for Minors?
Published on | Written by Alec Pow
This article was researched using 12 sources. See our methodology and corrections policy.
Federal claims data now put a dollar figure on a debate that has generated far more political attention than its share of the Medicaid budget.
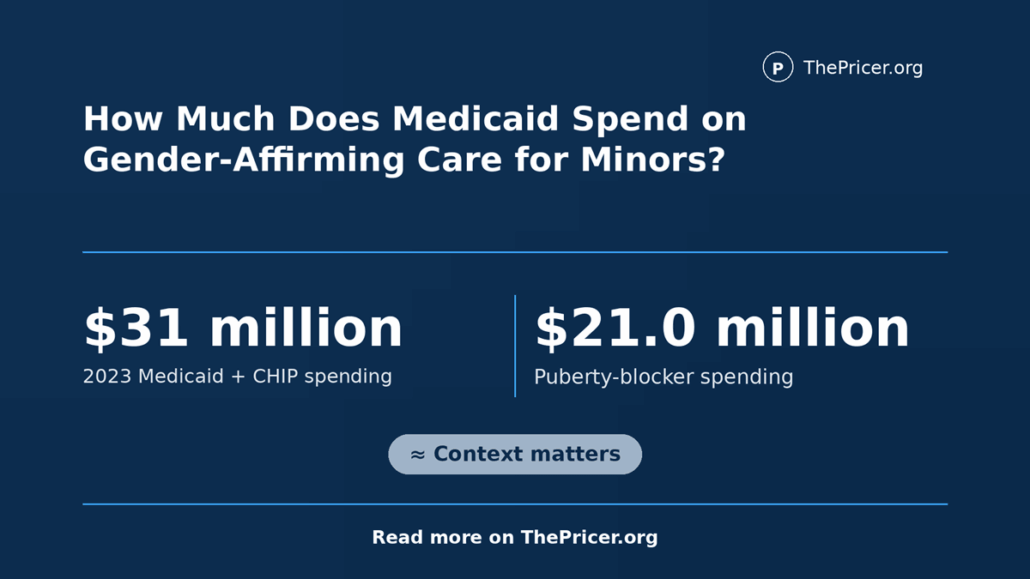
CMS identified about $31 million in combined Medicaid and CHIP spending in 2023 for the treatment categories covered by its new funding rule, according to the agency’s 2023 claims analysis. After adjusting the age data, CMS calculated $23.8 million in hormone spending for children ages 6 through 17. Puberty blockers accounted for $21.0 million of that amount, with another $2.8 million going to estrogen, anti-androgen drugs, and testosterone.
Those figures measure government insurance payments rather than the retail cost of treating one child. They also combine Medicaid and CHIP. Surgery, pharmacy claims, professional services, federal matching funds, state payments, and services financed outside those programs have different accounting paths.
TL;DR: Medicaid and CHIP spent about $31 million on the covered treatment categories in 2023, and CMS projects its new funding restriction will reduce combined government spending by $235 million over the next decade.
For readers following the money, the useful unit is annual Medicaid and CHIP claims spending. Treatment type and payer matter most because puberty blockers dominate the drug total and some spending may move to state-only funding after federal matching ends.
Important numbers
Jump to sections
- 2023 covered Medicaid and CHIP spending about $31 million (at $30 per hour, earning that amount would take about 497 years of full-time work, before taxes)
- Puberty-blocker spending for ages 6 through 17 $21.0 million
- Other hormone spending $2.8 million
- Projected 2027-2036 spending reduction $235 million
- Detailed federal share of that reduction $138 million
What this is in plain terms
Medicaid and CHIP are public health insurance programs financed by federal and state governments. The claims at issue here involve medications and procedures associated with treatment for gender dysphoria. CMS includes GnRH analogues used as puberty blockers, hormone therapy, and certain surgical claims in the spending analysis behind its 2026 rule.
This is not a price list for a family deciding whether to seek care. Claims reflect what public insurance programs paid across many beneficiaries, providers, pharmacies, and hospital settings. A 2026 JAMA Pediatrics claims study also examined gender-related care among youth enrolled in Medicaid and CHIP from 2019 through 2023. Medical services, coverage rules, and access differ across states, so a national spending figure cannot be converted into one patient price.
The $31 Million in 2023
CMS built its estimate from Transformed Medicaid Statistical Information System records, including fee-for-service claims and managed-care encounters. The agency selected claims carrying specified gender-dysphoria diagnosis codes and then looked for inpatient surgery, outpatient surgery, professional hormone services, and prescription hormone claims. The T-MSIS research documentation describes the national data files used for Medicaid and CHIP research.
CMS’s raw table totals $30,595,765 (about 490 years of full-time work at $30 per hour) for 2023, which the agency rounds to about $31 million. The raw age bands are 6 through 12, 13 through 14, and 15 through 18. CMS later adjusts the final group because the new Medicaid funding restriction applies below age 18. That age correction matters most when reading the surgery numbers.
| Spending category | 2023 public figure | What the number means |
|---|---|---|
| Puberty blockers | $21.0 million | Adjusted ages 6-17 |
| Other hormone therapy | $2.8 million | Adjusted ages 6-17 |
| Inpatient surgery claims | $180,553 | Raw table includes age 18 |
| Outpatient surgery claims | $2,184,142 | Raw table includes age 18 |
Worked example
The adjusted hormone total is $23.8 million. Puberty blockers account for $21.0 million, so $21.0 million ÷ $23.8 million = about 88.2%. The remaining hormone categories represent about 11.8% of the adjusted drug total.
Puberty Blockers
The strongest treatment-specific number in the federal record is $21.0 million (about 337 years of full-time work at $30 per hour) for GnRH analogues used as puberty blockers among beneficiaries ages 6 through 17. CMS calculated that amount after assuming one-quarter of spending in its 15-through-18 data band belonged to 18-year-olds. The agency says blockers made up 88% of the adjusted $23.8 million hormone total. That concentration matters because public discussion can make surgery appear to be the main Medicaid expense. The claims data point in another direction. Drug spending is much larger.
GnRH analogues also have medical uses unrelated to gender dysphoria, including treatment of precocious puberty. CMS did not classify every prescription for these drugs as spending covered by the rule. Its method selected claims tied to specified diagnoses and treatment categories. An independent Medicaid youth spending study provides another national claims-based view of puberty blockers, hormones, and surgery. That distinction prevents the $21.0 million figure from being read as the government’s spending on every pediatric GnRH prescription in 2023.
Surgery Spending Is Smaller
The raw CMS table records $180,553 in inpatient hospital claims involving surgery and $2,184,142 in outpatient hospital claims. Added together, that is $2,364,695. The problem is age. CMS groups ages 15 through 18 together in the displayed table, so some of the surgical spending belongs to 18-year-olds. The agency says it corrected for age when building its later regulatory estimates, but it does not publish a clean under-18 surgery total in that table. The final-rule public inspection record documents the scope and age limits.
The useful conclusion is narrower than some political claims from either direction. Public data show that surgical claims were far below hormone spending in 2023, but the exact minor-only surgical amount cannot be recovered from the displayed age bands. Hospital claims also differ from pharmacy spending because they can include facility services tied to an operation rather than only the physician’s work. Readers comparing public insurance with commercial plans can see the broader payer differences in ACA insurance costs, where the insurer, network, deductible, and service setting change who actually pays the bill.
Three Spending Cases
Drug case. Puberty blockers represent $21.0 million of adjusted 2023 hormone spending. Compared with the $2.8 million spent on the other named hormone categories, the blocker total is 7.5 times larger. That makes pharmacy and administered-drug policy a larger budget issue than the surgery claims visible in CMS’s table.
Hospital case. The raw inpatient and outpatient surgery lines total $2,364,695, but the age-band issue prevents that amount from being assigned entirely to minors. The case is useful because it shows why a headline can be technically wrong even when every dollar came from a government table.
State-payer case. A state that continues paying for covered services after federal matching disappears may replace part of the federal reduction with state-only spending. Current state policy tracking shows that youth access rules already differ sharply by jurisdiction. That means the same federal rule can produce a spending reduction in one state and a payer shift in another. The payer can change. The care does not automatically disappear everywhere.
The Rule’s Federal Savings
CMS projects that the final rule will reduce combined Medicaid and CHIP spending by $235 million from 2027 through 2036. The detailed schedule assigns $138 million of that reduction to federal spending and $97 million to state spending. Reuters calculated that the $138 million federal reduction equals roughly 0.002% of projected federal Medicaid and CHIP spending over the decade in its August 2026 rule report. That denominator changes how the fiscal argument reads.
Supporters of the rule can point out that CMS says it adopted the policy because of its assessment of medical evidence, risks, and federal payment standards rather than because it expected a large budget reduction. Opponents can point to the same denominator and argue that a policy affecting access for low-income patients produces an extremely small change in a program measured in trillions of dollars over a decade. The spending figure alone does not resolve the medical dispute, but it does establish the scale of the fiscal effect.
CMS itself says the rule was not adopted as a budget-saving measure. That makes the $235 million projection a consequence of the policy rather than its stated purpose.
90% of Public Comments on the Proposal
CMS received about 11,000 timely pieces of correspondence on the proposed Medicaid and CHIP rule. The agency says fewer than 10% supported the proposal and more than 90% opposed it, according to its public-comment summary. CMS still finalized the proposal with two changes. One created a limited six-month continuation period for existing patients receiving non-GnRH hormone therapy. The second revised regulatory wording around the definition used in the rule. Puberty blockers and surgery do not receive that six-month continuation period.
The comment split is newsworthy, but it does not tell readers whether the underlying medical evidence supports or opposes the rule. The administration says the evidence does not justify federal payment for the covered interventions in minors. The American Academy of Pediatrics takes a different position and says adolescents should have insurance access to gender-affirming care in its 2026 Medicaid policy statement. The American Medical Association also supports insurance coverage for treatment of gender dysphoria and opposes restrictions that remove clinical decisions from patients, families, and physicians through its current coverage policy.
The Projected Savings
 CMS acknowledges a major limitation in the savings estimate. States may finance these services without federal matching funds, private insurance may pick up some claims, and other healthcare spending could change after coverage is withdrawn. The agency says it could not quantify those effects. Its economic impact discussion says that if states or other payers keep covering the services, those payers would incur costs corresponding to some of the projected Medicaid and CHIP reductions.
CMS also acknowledges concerns about greater use of mental-health crisis services and other downstream costs but does not attach a national dollar estimate. That creates a limit on any claim that the rule will save taxpayers exactly $235 million. It is a projected reduction in Medicaid and CHIP spending under the agency’s assumptions. Some of that money could move to state budgets, private coverage, families, or other healthcare services rather than vanish from the healthcare system.
The final rule also contains an unusual accounting issue. One passage says federal Medicaid spending will fall by about $175 million from 2027 through 2036 in the opening economic estimate. The later detailed table gives $138 million in federal Medicaid and CHIP reductions. The document does not explicitly reconcile the two figures. Table 4 says its figures incorporate updated assumptions, including the six-month continuation period and changes in states that had already restricted coverage. Reuters also reports $138 million. For that reason, $138 million is the stronger figure for the final federal projection.
What we verified
- Checked the August 2026 HHS announcement confirming that the rule takes effect October 13 and concerns federal Medicaid and CHIP funding.
- Confirmed the KFF funding analysis explaining that states can use state-only dollars where state law permits coverage.
- Cross-referenced the AMA’s CMS comments opposing the proposed Medicaid funding restriction.
Who this cost makes sense for
The federal figures are useful when the question is how much public insurance paid and how much CMS expects its rule to remove from Medicaid and CHIP spending. They are less useful for deciding what one patient’s treatment costs or whether a treatment is clinically appropriate. The fiscal record says puberty blockers were the largest named drug category, surgery spending was smaller, and the projected federal savings are tiny compared with the full Medicaid and CHIP budget.
The medical dispute remains separate. HHS argues that the evidence and risk profile do not support federal funding for the covered interventions in minors. Major physician groups dispute that conclusion and support access to gender-affirming care. Medicaid policy can also create costs beyond medical claims, as seen with Medicaid work requirement spending, where federal savings, state administration, and patient costs sit on different ledgers.
Makes sense if
- You want claims-based Medicaid and CHIP spending figures.
- You need puberty blockers separated from other hormone spending.
- You are comparing federal savings with state cost shifts.
- You want the fiscal scale separated from the clinical debate.
Doesn’t make sense if
- You need a per-patient treatment quote.
- You need Medicaid spending with CHIP fully removed.
- You want a clean under-18 surgery total from the raw table.
- You are using spending alone to judge medical benefits or risks.
Article Highlights
- CMS identified about $31 million in combined Medicaid and CHIP spending for the covered treatment categories in 2023.
- Puberty blockers accounted for $21.0 million, or about 88% of adjusted hormone spending.
- CMS projects $235 million less Medicaid and CHIP spending from 2027 through 2036.
- The detailed federal reduction is $138 million, roughly 0.002% of projected federal Medicaid and CHIP spending over the decade.
- More than 90% of roughly 11,000 public comments opposed the proposed rule.
- CMS does not quantify how much projected savings could shift to state budgets, private insurance, families, or other healthcare services.
Answers to Common Questions
How much did Medicaid spend on puberty blockers for minors?
CMS calculated about $21.0 million in combined Medicaid and CHIP spending on GnRH analogues for beneficiaries ages 6 through 17 in 2023 after adjusting its age data.
How much did Medicaid and CHIP spend on the covered care in total?
CMS identified about $31 million in total federal and state Medicaid and CHIP spending in the 2023 claims categories used for the rule.
How much will the new rule save?
CMS projects a $235 million reduction in combined Medicaid and CHIP spending from 2027 through 2036, including $138 million in federal spending and $97 million in state spending.
Does the rule ban gender-affirming care nationwide?
No. It changes federal Medicaid and CHIP funding. States may face separate state laws and can use state-only funding where their laws and policies permit it.
Disclosure: Educational content, not medical advice. Pricing varies by provider, location, and insurance. Confirm eligibility, coverage, and out-of-pocket costs with a licensed clinician and your insurer. See our methodology and corrections policy.