
How Much Does a Blood Transfusion Cost?
Updated on | Written by Alec Pow
This article was researched using 7 sources. See our methodology and corrections policy.
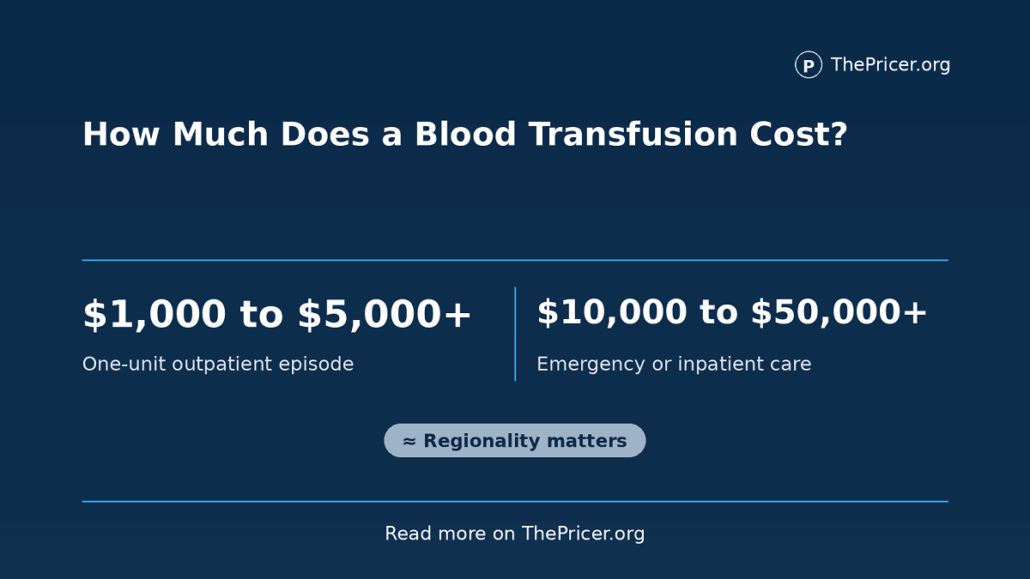
A one-unit outpatient red blood cell transfusion can generate total hospital charges or self-pay costs of roughly $1,000 to $5,000+ in the United States. The complete bill may include the blood component, blood typing, antibody screening, crossmatching, processing, intravenous supplies, nursing administration, monitoring, facility charges, and follow-up laboratory work.
With insurance, a patient may owe from $0 to several thousand dollars, depending on the deductible, coinsurance, network, treatment setting, and annual out-of-pocket maximum. A transfusion given during emergency surgery, trauma treatment, childbirth, cancer care, or an inpatient admission may be only a small line item within a total hospital bill of $10,000 to $50,000+.
There is no reliable national retail price for “one unit of blood.” Hospitals bill the blood product and transfusion-related services separately, and the amount charged is not necessarily the amount accepted from an insurer or Medicare.
Article Highlights
Jump to sections
- A one-unit outpatient red blood cell episode may cost about $1,000 to $5,000+ (at $30 per hour, earning that amount would take about 0.8 to 4.2 full-time workweeks, before taxes).
- Multiple units, emergency care, surgery, or hospitalization can raise the total into the tens of thousands.
- A red blood cell unit is normally about 300 to 400 mL, not a fixed 525 mL.
- The donated blood itself is only one part of the bill.
- Testing, processing, administration, monitoring, and facility care may cost more than the blood component.
- For many stable hospitalized adults, clinicians consider transfusion near a hemoglobin level of 7 g/dL, but the decision is individualized.
- Original Medicare covers medically necessary blood services, with different patient costs for inpatient and outpatient care.
How Much Does a Blood Transfusion Cost?
| Transfusion expense | Planning price | What it covers |
|---|---|---|
| Pre-transfusion laboratory testing | $150 to $600+ (about 0.6 to 2.5 full-time workdays at $30 per hour) | Complete blood count, blood typing, antibody screen, and crossmatch |
| Red blood cell product and processing | $300 to $1,000+ | Blood component, testing, preparation, storage, and handling |
| Transfusion administration | $400 to $2,000+ | IV access, supplies, nursing time, verification, and monitoring |
| Outpatient facility charges | $500 to $2,500+ | Treatment space, hospital overhead, equipment, and observation |
| Follow-up laboratory testing | $50 to $300+ | Repeat blood count or other tests after transfusion |
| One-unit outpatient episode | $1,000 to $5,000+ | Combined blood product, laboratory, administration, and facility services |
| Emergency or inpatient episode | $10,000 to $50,000+ | Transfusion plus emergency care, procedures, surgery, or hospitalization |
These ranges are planning estimates, not fixed national fees. Hospital gross charges, discounted cash prices, insurer-negotiated rates, and Medicare payments can all differ for the same service.
Federal hospital price-transparency rules require hospitals to disclose standard charges, including discounted cash prices where offered. The current CMS hospital price-transparency program can help patients locate a hospital’s machine-readable price file or consumer cost-estimator tool.
When a transfusion is considered
A blood transfusion may be used for severe anemia, active blood loss, surgery, trauma, cancer treatment, bone marrow disorders, childbirth complications, or another condition affecting blood cells or clotting.
The old version of this article incorrectly stated that transfusions are given when hemoglobin drops below 70 to 80 mg/dL. Hemoglobin is normally reported in grams per deciliter. The intended numbers would have been 7 to 8 g/dL, but even that is not an automatic rule.
AABB recommends considering a restrictive red blood cell transfusion strategy near 7 g/dL for many hemodynamically stable hospitalized adults. Different thresholds may be considered for some orthopedic, cardiac, or cardiovascular patients. The organization’s transfusion threshold summary stresses symptoms and clinical context rather than using one number for every patient.
Active bleeding, chest pain, shortness of breath, blood pressure, heart disease, oxygen needs, laboratory trends, and the likely cause of anemia can all affect the decision. A patient should not use an online hemoglobin threshold to decide whether to seek or refuse urgent treatment.
What one unit means
Modern transfusions usually provide a blood component rather than an entire bag of whole blood. The most common components are:
- Red blood cells for anemia or blood loss
- Platelets for low platelet counts or impaired clotting
- Plasma for selected clotting-factor deficiencies
- Cryoprecipitate for fibrinogen and certain clotting needs
- Whole blood in selected trauma and massive-bleeding situations
The American Red Cross states that a red blood cell product commonly has a volume of about 300 to 400 mL per unit. The exact volume varies with the donor and processing method. Its red blood cell product specifications also explain that a unit contains concentrated red cells, preservative solution, and a limited amount of donor plasma.
A platelet transfusion is not priced or dosed in the same way as a red blood cell unit. Plasma and cryoprecipitate also have their own product, laboratory, and administration codes. Ask which component appears on the estimate before comparing prices.
Why donated blood is not free
Blood donors are not normally paid for a standard volunteer donation, but collecting and delivering a safe transfusion involves substantial work.
Before a component reaches the patient, blood centers and hospitals may need to cover:
- Donor recruitment and collection
- Infectious-disease testing
- Blood typing and component separation
- Leukocyte reduction or other processing
- Refrigerated transport and storage
- Inventory management and discarded expired products
- Patient-specific compatibility testing
- Clinical administration and observation
AABB’s blood-product billing guide shows that hospitals report blood products, transfusion administration, and patient-specific laboratory work under separate codes. A hospital is not simply charging for a donated bag.
The American Red Cross supplies millions of blood products to hospitals and says nearly 16 million blood components are transfused annually in the United States. Its current U.S. blood supply data uses components rather than treating every transfusion as whole blood.
Why a $300 component becomes $3,000
Consider a simplified scheduled outpatient red blood cell transfusion:
- Blood count, type, screen, and crossmatch: $350 (about 1.5 full-time workdays at $30 per hour)
- Red blood cell component and processing: $600
- Transfusion administration and supplies: $900
- Outpatient facility and monitoring: $1,200
- Repeat laboratory work: $150
The episode reaches $3,200, even though the blood component accounts for only $600. This is a calculated scenario based on common billing categories, not a universal hospital fee schedule.
A second red blood cell unit may add another product and processing charge, but the total does not always double. Some laboratory, IV, facility, and administration work is shared across the same treatment visit.
Outpatient versus emergency costs
A scheduled outpatient transfusion may take place in a hospital infusion unit, hematology clinic, cancer center, or another medically supervised setting. The patient normally arrives with laboratory orders and an established treatment plan.
An emergency transfusion is different. The patient may also require:
- Emergency department evaluation
- Ambulance transport
- Imaging and repeated laboratory tests
- Endoscopy, surgery, or another procedure
- Intensive care or inpatient admission
- Multiple blood components
- Treatment of shock or organ injury
A transfusion used during a gastrointestinal bleed may cost less than the endoscopy, hospital stay, medications, and treatment of the bleeding source. A unit administered during trauma surgery may be one small part of a bill above $50,000.
Someone comparing emergency expenses may also need to account for the cost of an emergency room visit or an ambulance ride. Those services are billed separately from the blood product.
What insurance may leave you owing
Private health insurance generally covers a medically necessary transfusion, but coverage does not mean the service is free. The patient may still owe a deductible, copayment, coinsurance, or charges for services outside the plan’s network.
Consider an outpatient transfusion with an insurer-negotiated allowed amount of $3,000. The patient has $1,000 left on the deductible, followed by 20% coinsurance:
- Remaining deductible: $1,000
- Balance after deductible: $2,000
- 20% coinsurance: $400
The patient responsibility would be approximately $1,400, provided every service is in-network and the annual out-of-pocket maximum does not lower the amount.
The calculation normally uses the allowed amount, not the hospital’s full billed charge. A hospital might list $7,000 in gross charges while accepting a much lower negotiated amount from the insurer.
How Medicare covers blood
Original Medicare covers medically necessary blood and blood-processing services under different rules depending on whether the patient is admitted as an inpatient or treated as an outpatient.
Medicare’s blood services coverage page states that Part A covers processing and handling for an inpatient. After the Part A deductible, there is no separate copayment for blood processing and handling during the inpatient stay.
For hospital outpatient care, Part B covers blood processing and handling. After the Part B deductible, the patient pays an applicable hospital copayment for each unit. The exact copayment depends on the services and setting.
The standard Medicare Part B deductible is $283 in 2026. Medigap coverage may pay some Original Medicare deductibles, copayments, or the first three pints of blood, depending on the policy. Medicare Advantage plans use their own networks, authorizations, copays, and annual limits.
Medicare also describes special rules for the first three units when the provider must purchase blood rather than receiving it through donation or replacement. The hospital’s billing department or the patient’s plan should explain how those rules apply to the specific admission.
Testing before the transfusion
Before compatible blood can be issued, staff confirm the patient’s identity and complete required laboratory work. Testing may include:
- Complete blood count
- ABO and Rh blood type
- Antibody screen
- Crossmatch with donor blood
- Additional antibody identification where needed
Patients with previous transfusions, pregnancy history, or certain antibodies may need more complex matching. That can extend preparation time and add laboratory costs.
The IV line, tubing, filters, saline, medications, and nursing time may appear under separate billing categories. A TB test is not part of routine transfusion compatibility testing and should not be used as a comparison for the specialized blood-bank work involved.
How long it takes
A simple blood transfusion may take about one to four hours, depending on the blood component, amount ordered, clinical urgency, and the patient’s condition. The Red Cross describes this range in its transfusion procedure overview.
Staff usually check temperature, blood pressure, pulse, and other vital signs before and during the transfusion. The infusion may be slowed or stopped if a reaction is suspected.
A patient receiving scheduled outpatient care may leave after the required monitoring period. A patient treated for active bleeding, surgery, severe anemia, or another serious condition may remain under observation or stay in the hospital.
Possible reactions and added costs
Modern transfusion practices make serious complications uncommon, but no transfusion is risk-free. Possible reactions include fever, allergy, hemolysis, fluid overload, breathing complications, or the development of antibodies that affect future matching.
Additional evaluation may involve:
- Stopping the transfusion
- Repeat blood-bank testing
- Laboratory work and urine testing
- Medication or oxygen
- Chest imaging
- Longer observation or admission
Infectious-disease transmission is possible but uncommon because donated blood undergoes screening and testing. It should not be presented as the normal reason transfusion bills become expensive.
Blood type and compatibility
AB negative is the least common of the eight main ABO and Rh blood types in the United States, but an AB-negative patient does not necessarily require AB-negative red cells.
AB-negative patients can generally receive compatible Rh-negative red blood cells from O negative, A negative, B negative, or AB negative donors. Plasma compatibility follows different rules, which is why the hospital blood bank selects the component rather than relying on a simple universal chart.
O-negative red blood cells are often used in emergencies when there is not enough time to establish the recipient’s blood type. Exact matching and conservation policies can change once laboratory results are available.
The hidden cost is the cause
A transfusion raises or replaces a blood component. It does not automatically correct the reason the patient became anemic or started bleeding.
The underlying treatment may include:
- Iron therapy for iron-deficiency anemia
- Endoscopy for gastrointestinal bleeding
- Surgery for trauma or internal bleeding
- Cancer treatment
- Management of kidney or bone marrow disease
- Care following childbirth complications
A patient with iron deficiency may also compare the transfusion episode with the cost of an iron infusion, although the treatments are not interchangeable. A transfusion is used when clinicians need to replace blood cells more directly or urgently, while iron supports the body’s production of new red blood cells when iron deficiency is the cause.
Help with an uninsured bill
A scheduled outpatient transfusion may allow time to request a written estimate. Ask for the expected codes for the blood product, laboratory work, transfusion administration, and facility.
An uninsured patient can also ask about:
- Discounted cash pricing
- Hospital financial assistance
- Medicaid eligibility
- Interest-free payment plans
- Nonprofit hospital charity-care policies
- A good-faith estimate for scheduled care
Do not delay emergency treatment because of price. Active bleeding, severe weakness, chest pain, trouble breathing, fainting, confusion, or another serious symptom requires medical evaluation first. Financial assistance and billing review can follow after the patient is stable.
A self-pay discount of “up to 50%” should not be assumed. Discounts vary by hospital, income, service, and whether the patient completes a financial-assistance application.
What to ask before scheduled care
- Checked which blood component and how many units were ordered.
- Confirmed whether the transfusion is outpatient, observation, or inpatient care.
- Requested an estimate covering laboratory work, blood product, administration, and facility fees.
- Verified that the hospital, ordering doctor, and related providers are in-network.
- Asked whether follow-up blood tests are included or billed separately.
- Applied for financial assistance before the appointment when eligible.
Answers to Common Questions
How much does one unit of blood cost at a hospital?
The blood component and processing may account for several hundred dollars, but a one-unit outpatient transfusion can cost $1,000 to $5,000+ after laboratory, administration, monitoring, and facility charges are added.
How much does a blood transfusion cost with insurance?
Patient responsibility can range from $0 to several thousand dollars. The result depends on the allowed amount, deductible, coinsurance, network status, and out-of-pocket maximum.
Does Medicare cover blood transfusions?
Yes, when medically necessary. Part A generally applies during inpatient care, while Part B covers outpatient processing and handling. Deductibles and copayments can still apply.
At what hemoglobin level is a transfusion needed?
There is no automatic level for every patient. For many stable hospitalized adults, clinicians consider a restrictive threshold near 7 g/dL, while symptoms, bleeding, heart disease, surgery, and other factors may change the decision.
How long does a blood transfusion take?
A simple transfusion commonly takes about one to four hours. Multiple units, slower infusion rates, reactions, or the underlying condition can extend the visit.
Disclosure: Educational content, not medical advice. Pricing varies by provider, location, and insurance. Confirm eligibility, coverage, and out-of-pocket costs with a licensed clinician and your insurer. See our methodology and corrections policy.