
How Much Does Epidural Steroid Injection Cost?
Updated on | Written by Alec Pow
This article was researched using 11 sources. See our methodology and corrections policy.
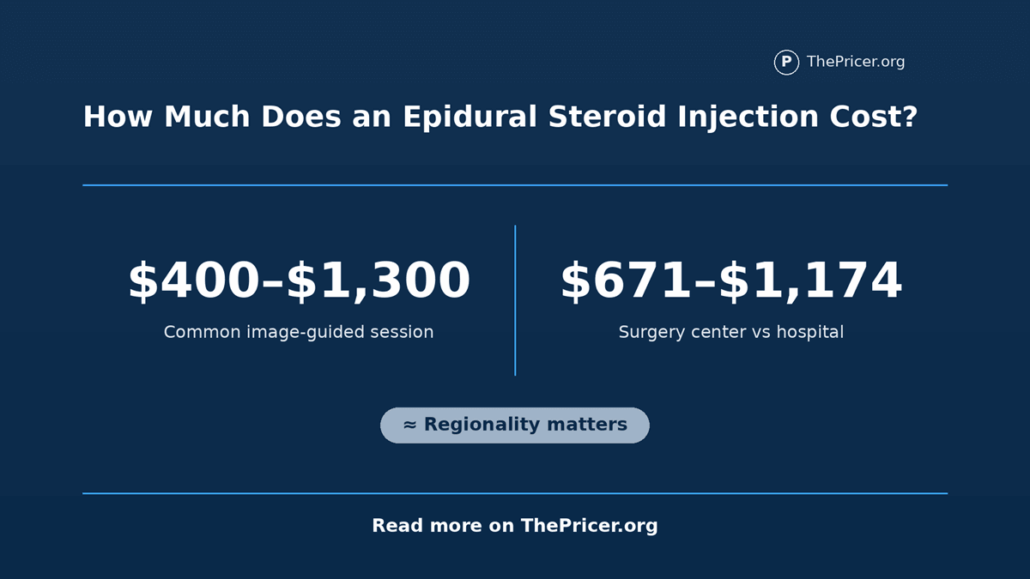
An image-guided epidural steroid injection costs about $400 to $1,300 in many current cash-price examples, while published listings extend from $359 for some in-office procedures to $2,970 for facility-based care. A surgery-center benchmark is $671, compared with $1,174 at a hospital outpatient department. The amount is usually quoted per treatment session, not as a guaranteed multi-injection package.
The payable total depends on the spinal region, injection approach, number of treated levels, site of care, imaging guidance, insurance contract, remaining deductible, and whether the quote bundles the physician and facility. A low professional fee can become a much larger bill when fluoroscopy, a hospital facility, consultation, diagnostic imaging, or an additional level is charged separately.
Epidural steroid injection pricing should be compared by complete session and site of care. Office, ambulatory surgery center, and hospital outpatient prices do not include the same billing structure.
Interlaminar, transforaminal, and caudal injections also use different procedure codes and level rules. A price for one lumbar level should not be compared with a cervical procedure, bilateral treatment, or an additional nerve-root level without checking the full scope.
Article Highlights
Jump to sections
- Common current cash band: about $400 to $1,300 (at $30 per hour, earning that amount would take about 0.3 to 1.1 full-time workweeks, before taxes) per image-guided session
- In-office published range: $359 to $1,399
- Surgery-center cash benchmark: $671
- Hospital outpatient cash benchmark: $1,174
- Facility-based listings: $700 to $2,970
- Main billing traps: split physician and facility claims, added levels, consultation, MRI or CT, exceptional sedation, and deductible exposure
- No automatic series: repeat treatment should follow documented response rather than a preset package of three to six injections
How Much Does an Epidural Steroid Injection Cost?
| Price setting | Current price signal | What the number represents |
|---|---|---|
| In-office image-guided injection | $359 to $1,399 (about 0.3 to 1.2 full-time workweeks at $30 per hour) | Published MDsave listings for office-based care |
| Ambulatory surgery center | $671 | Average cash price with $158 provider and $513 facility portions |
| Hospital outpatient department | $1,174 | Average cash price with $158 provider and $1,016 facility portions |
| Facility-based image-guided listings | $700 to $2,970 | Wide prepaid range across participating providers |
| Published flat-rate package | $1,265 | Named package including physician, facility, and anesthesia charges |
MDsave currently lists in-office image-guided prices from $359 to $1,399. Its broader facility-based injection listings run from $700 to $2,970. These are prepaid offers from participating providers, not one national required fee.
Sidecar Health reports an average surgery-center cash price of $671 and an outpatient-hospital price of $1,174. The hospital figure is $503 higher, about 75% above the surgery-center total.
What This Is in Plain Terms
An epidural steroid injection places corticosteroid medication, often with local anesthetic or saline, into the epidural space near irritated spinal nerve roots. It is not an injection into the spinal cord. The procedure may be performed in the cervical, thoracic, lumbar, or sacral region, depending on the diagnosis and symptoms.
An interlaminar injection enters between the vertebral laminae near the middle of the spine. A transforaminal injection approaches through the opening where a nerve root exits. A caudal injection enters through the sacral hiatus near the base of the spine. These routes are not interchangeable billing labels.
Diagnostic MRI or CT may identify the suspected nerve compression before treatment. During the injection, fluoroscopy or CT and contrast are commonly used to confirm needle placement. Local numbing medication is routine. Moderate sedation, deep sedation, general anesthesia, or monitored anesthesia care is not a standard requirement for most sessions.
The Same Injection With Different Bills
The largest difference often comes from the site of care. In Sidecar’s data, the physician portion remains $158 (about 5.3 hours of work at $30 per hour) in both settings. The facility portion rises from $513 at a surgery center to $1,016 at a hospital outpatient department. The extra $503 comes from the facility, not a different provider fee.
An office may publish only its professional rate. Center for Interventional Pain and Spine lists a lumbar epidural steroid injection at $310 and fluoroscopy at $114 on its current self-pay schedule. If both lines apply separately, the worked office total is $424. The patient still needs to ask whether medication, contrast, supplies, and any outside facility are included.
Hidden price: “injection fee” may mean the physician’s work only. Ask whether the written quote includes the facility, fluoroscopy or CT guidance, contrast, medication, recovery monitoring, and every treated level.
An additional level can create another charge. Current additional-level listings span $74 to $1,650. That wide range is a reason to obtain the exact procedure code and level count before scheduling.
A flat-rate package can make the scope easier to read. NTTC Surgery Center posts a $1,265 cash injection package that includes physician, facility, and anesthesia fees. That package should not be compared with a $310 professional line unless both quotes cover the same services.
What Insurance Changes
Insurance replaces the cash price with the plan’s negotiated allowed amount. The patient may owe a deductible, copay, coinsurance, noncovered service, or out-of-network balance. A person who has not met a high deductible can owe most or all of the negotiated price even when the procedure is covered.
For CPT 62323, Medicare’s current outpatient procedure lookup shows an approved total of $476 at an ambulatory surgical center and $810 at a hospital outpatient department. Under Original Medicare, the patient usually pays 20% after the Part B deductible, which works out to about $95 versus $162 before Medigap, Medicaid, employer retiree coverage, or another secondary payer.
The Medicare amounts are national estimates, not promises for a specific claim. Cervical, transforaminal, bilateral, additional-level, consultation, and diagnostic imaging codes can produce different totals. Medicare Advantage and private plans may require prior authorization, in-network providers, documented conservative treatment, and diagnosis-specific criteria.
Before the appointment, request the procedure codes, diagnosis code, place-of-service code, provider network status, facility network status, and written estimate. Ask the insurer whether the physician and facility will submit separate claims. A quoted copay is not enough when the deductible or coinsurance applies to one of those claims.
A Series Is the Wrong Price Model
A preset series of three to six injections should not be treated as the normal budget. The current Medicare coverage policy says a predetermined series is not medically reasonable and necessary. It limits coverage to four sessions per spinal region in a rolling 12-month period and bases repeat treatment on documented improvement or a medically explained change in approach after an inadequate first response.
The same policy calls for fluoroscopy or CT guidance with contrast in ordinary covered cases. Ultrasound without contrast is reserved for limited circumstances such as documented contrast allergy or pregnancy. It also states that moderate or deep sedation, general anesthesia, and monitored anesthesia care are usually unnecessary or rarely indicated.
Expected benefit should be framed carefully. A 2025 American Academy of Neurology review found limited efficacy, with the strongest evidence centered on short-term pain and disability improvement for radiculopathy. Evidence for long-term pain relief was insufficient, and the findings were less certain for some spinal-stenosis settings.
The FDA also warns of rare but serious neurologic events after epidural corticosteroid administration and notes that corticosteroids are not approved specifically for epidural use in its epidural injection safety record. That warning belongs in the cost decision because a low price does not replace clinical eligibility, informed consent, or a qualified image-guided provider.
Three Realistic Patient Bills
Case 1: Office self-pay session. A published lumbar procedure fee of $310 plus separate fluoroscopy at $114 produces an estimated $424 bill. At a wage of $30 per hour, that equals about 14 hours of work. The patient must verify whether the office fee includes the steroid, contrast, supplies, and recovery monitoring.
Case 2: Surgery-center cash patient. The national cash benchmark combines a $158 provider fee and $513 facility fee for an all-in total of $671. That equals about 22 hours of work at $30 per hour.
Case 3: Hospital outpatient patient. The provider remains $158, while the facility reaches $1,016. The total is $1,174, equal to about 39 hours of work at $30 per hour. The hospital setting costs $503 more than the surgery-center benchmark.
These scenarios are not treatment recommendations. They show why the patient should compare complete sessions rather than one line item. The appropriate setting and procedure depend on clinical needs, available support, insurer rules, and the clinician’s plan.
When This Cost Makes Sense
Makes sense to price and discuss if:
- A clinician has identified radicular pain, radiculopathy, or neurogenic claudication tied to spinal pathology.
- The symptoms and imaging support the same spinal region and nerve distribution.
- Conservative treatment has failed, cannot be tolerated, or is not appropriate under the payer’s policy.
- The provider uses the required image guidance and supplies an itemized estimate.
- A repeat session is based on the measured response to the prior injection, not a prepaid automatic series.
Does not make sense if:
- The quote is for a vague “back pain injection” without the route, level, region, and procedure code.
- An office fee is being compared with a bundled hospital or surgery-center total.
- The patient is told to choose ultrasound, sedation, or a different provider solely because it is cheaper.
- The facility cannot explain prior authorization, network status, or separate billing.
- A package requires payment for several injections before the response to the first session is known.
What We Verified
- Checked: Current Medicare policy requires CT or fluoroscopy guidance with contrast in ordinary cases and does not support a predetermined injection series.
- Confirmed: The 2026 Medicare lookup shows a lower approved amount at an ambulatory surgery center than at a hospital outpatient department for CPT 62323.
- Cross-referenced: The 2025 neurology review supports limited short-term benefit for selected radiculopathy patients rather than a universal success rate.
- Verified: Preparation can include fasting, medication adjustments, diagnostic imaging, and transportation when sedation is planned, according to current epidural injection instructions. Patients should follow the treating facility’s written directions and should not stop blood thinners without prescriber guidance.
Related Spine Treatment Costs
The price comparison should match the diagnosis and complete treatment episode. Review the potential expense of back surgery, the separate billing that can appear with anesthesia services, and the much larger trial and implant costs of a spinal cord stimulator. These treatments serve different patients and should not be treated as interchangeable price tiers.
Answers to Common Questions
How much is one epidural steroid injection without insurance?
Current image-guided cash examples commonly fall around $400 to $1,300, while published listings extend from $359 to $2,970. The facility and included services explain much of that spread.
Does Medicare pay for epidural steroid injections?
Original Medicare may cover a medically necessary injection that meets the applicable coverage policy. The patient usually owes 20% of the approved amount after the Part B deductible, subject to secondary coverage and the final claim.
How many injections will insurance cover?
There is no universal answer. One current Medicare policy limits treatment to four sessions per spinal region in 12 months and rejects a preset series. Private and Medicaid rules vary by plan and state.
Do patients need to fast before the procedure?
Some facilities require fasting, especially when sedation is planned. Others provide different instructions. Follow the written directions from the treating facility and ask how to handle diabetes medication, blood thinners, supplements, food, and transportation.
Is anesthesia included in the price?
Local numbing medication is part of the normal procedure. Deeper anesthesia or monitored sedation is not routine, but one cash package may include it. Ask whether any anesthesia service is planned and whether it will create a separate claim.
Disclosure: Educational content, not medical advice. Pricing varies by provider, location, and insurance. Confirm eligibility, coverage, and out-of-pocket costs with a licensed clinician and your insurer. See our methodology and corrections policy.
Sincerely for whatever personal reasons I need to get an epidural steroid injection for my wife in her neck. She has to have mri and x rays since few years showing her condition. I am willing to pay up to $3000 and I am here in Inland Empire. Southern California but we are willing and able to travel to any other state. My phone number is 909 677 6067. Maybe someone has an advice in how I can do this. I appreciate any advices, contacts, recommendations, etc. Thanks and happy holy days!
That sound good for me